
Healthcare trends: What to act on first

Contents
The healthcare trends that matter now are the ones an organization can deliver: ambient documentation, remote and home-based care, value-based contracts, and the cost pressure behind all of them. Each depends on plumbing that gets less attention, namely FHIR interoperability and cyber resilience.
This ranking is written for provider executives, payer strategists and healthtech product leaders choosing where to invest. Which two or three trends to act on first depends on whether you carry clinical, financial or product risk.
What are the latest trends in healthcare?
The healthcare trends shaping investment now are ambient clinical documentation, remote patient monitoring, hospital at home, and value-based care, all pressured by a rising medical cost trend. Each one stalls at a predictable point: EHR write-back depth, reimbursement, or no clear owner for the alert.
Netguru designs and builds healthcare software, including remote monitoring, connected-device and interoperability-heavy products for health organizations.
We recommend starting with the trend that already has a payment path and a scoped EHR integration, because integration depth and clinical ownership decide how fast a pilot reaches production. Payers should read the table from the cost and value-based care rows first.
Teams without in-house integration experience can use healthcare software consulting to scope the EHR work and the clinical ownership model before a pilot.
The trends side by side:
| Trend | What changes | Who it affects | Main barrier |
|---|---|---|---|
| Ambient clinical documentation | Visit audio becomes a draft note | Providers, EHR vendors | Clinician edit burden, shallow EHR write-back, patient consent |
| AI in diagnostics and imaging | Algorithms triage and read scans | Radiology, health systems | Validation and governance |
| Remote patient monitoring | Home device readings feed care teams | Providers, payers, device makers | Alert fatigue, device logistics, triage ownership |
| Hospital at home | Acute care moves into the home | Health systems, payers | Nursing model, escalation protocols |
| Virtual care in hybrid models | Telehealth runs alongside in-person visits | Providers, patients | Consistent experience across channels |
| Value-based care | Payment tied to outcomes and risk | Providers, payers | Outcome measurement, data capability |
| FHIR interoperability | Standard APIs for data exchange | Product teams, health systems | R4 and US Core variance across EHR vendors |
| Ransomware attacks on providers | Downtime planning enters technology roadmaps | Providers | Recovery readiness |
| Medical cost trend | Spending growth, with pharmacy and GLP-1 pressure | Payers, employers, providers | Few controllable levers within a plan year |
Which healthcare industry trends matter most for investment?
The healthcare trends that matter most for investment depend on two conditions: how much financial risk your organization carries, and how ready its data is to move between systems. Risk decides which trend pays back. Data readiness decides how soon.
The medical cost trend sets the backdrop for every row below. US national health expenditure is projected to grow 5.4 percent a year on average over 2025-34, ahead of GDP growth of 4.1 percent (CMS National Health Expenditure fact sheet).
The ranking by role, side by side:
| Role | Deciding condition | Act on first | Act on second |
|---|---|---|---|
| Provider, mostly fee-for-service | Clinician time and margin | Generative AI in clinical administration (ambient documentation) | FHIR interoperability for EHR write-back |
| Provider, two-sided risk | Cost of avoidable admissions | Value-based care analytics | Remote patient monitoring for high-risk panels |
| Payer | Medical cost trend and claims leakage | FHIR interoperability for clinical data exchange | Value-based care contract operations |
| Product team | Data readiness | FHIR interoperability (US Core, SMART on FHIR) | Generative AI in administrative workflows |
We recommend product teams hold remote monitoring until a named clinical owner exists for every alert. Payers should add generative AI for prior authorization and claims review only after the data exchange work above is in place.
This ranking assumes a US market and does not weigh security spend. Ransomware exposure can move data engineering and recovery planning to the top of any row, whatever your risk position.
How is generative AI changing clinical documentation?
Generative AI is changing clinical documentation by turning recorded visit audio into draft notes, which targets the charting load behind clinician burnout. Ambient clinical documentation is generative AI in clinical administration: it drafts text a clinician reviews and signs. Diagnostic AI, which reads images or flags disease, sits under separate FDA oversight and a different risk profile.
Early evidence points to lower burnout. In a 2025 study across six US health systems, burnout among ambulatory clinicians fell from 51.9% to 38.8% after 30 days of ambient AI scribe use (Olson et al., JAMA Network Open, 2025). The study had no control group and relied on surveys before and after, so treat it as an early signal.
A vendor demo will not show where pilots break. Four failure modes recur, and each has a measurable sign:
| Failure mode | What breaks | How to spot it in a pilot |
|---|---|---|
| Specialty fit | Note templates tuned to primary care miss the structure of behavioral health, surgery, or pediatrics | Report results per specialty, never pooled |
| Clinician edit burden | Typing time becomes review time, and the note takes as long as before | Compare after-hours EHR time from audit logs against each clinician's baseline |
| Shallow EHR write-back | The draft lands as free text, so medications, orders, and problem-list updates are re-entered by hand | Count manual copy-paste steps per visit; check whether output arrives as discrete FHIR resources or only a note attachment |
| Patient consent gaps | Audio is recorded without a documented opt-in | Audit a sample of encounters for a consent record |
Consent deserves its own review. Some US states require all-party consent for recording, and the audio is protected health information, so retention and vendor access terms belong in the BAA.
We recommend a 6-8 week pilot across at least three specialties, with edit time and write-back depth as the exit criteria. Teams building their own pipelines can start from AI development services.
Where is AI in diagnostics and imaging in use?
The FDA AI-enabled medical device list shows diagnostic and imaging AI in clinical use mostly in radiology, with other specialties trailing.
By January 2025, the FDA had authorized more than 1,000 AI-enabled devices through established premarket pathways (FDA, January 2025).
Authorization is where adoption starts, not where it ends. FDA clearance means a device met a regulatory bar. It does not show that the model performs on your scanners, your patient mix or your reading workflow.
That gap separates imaging AI from ambient documentation. A scribe drafts text a clinician reviews and signs, while an imaging model can change what a radiologist sees first and what gets missed. The CTO decision is two tracks with different gates:
| Attribute | Administrative AI (ambient documentation) | Regulated diagnostic AI (imaging) |
|---|---|---|
| Regulatory status | Generally outside device review when a clinician signs the output | FDA-authorized device, scope limited to its cleared indication |
| Main failure | Wrong or invented note text | Missed or false findings |
| Gate before go-live | Pilot with clinician review of drafts | Local validation on retrospective cases from your own scanners |
| Integration | EHR write-back | PACS and worklist integration, plus reporting back to the EHR |
| Owner | Clinical operations and IT | Radiology leadership with a governance committee |
We recommend sequencing administrative AI first and running imaging AI as a governed pilot in one service line, with a named radiology owner and drift monitoring after launch. Building that validation pipeline is data engineering work as much as model work.
Health systems with an imaging informatics team and a radiology champion can run both tracks in parallel. Without them, the second track is where projects stall.
Healthcare cost trends: What is driving medical cost growth?
Medical cost trend is driven by unit prices, utilization, and pharmacy spend, and only part of that growth sits within a payer's or provider's control. Forecasts report the total. The useful question is which components your organization can move.
CMS National Health Expenditure projections show health spending's share of GDP rising over the coming decade, with Medicare Advantage taking a growing share of Medicare enrollment.
The split below is our own judgment, not a published model:
| Driver | Payers | Providers |
|---|---|---|
| Controllable | Benefit and formulary design, site-of-care steering, network choices, prior authorization rules | Agency labor use, length of stay, supply chain automation, denial management, administrative workload |
| External | Provider price increases and consolidation, specialty drug list prices, behavioral health demand | Wage inflation, drug and device prices, payer mix shifting toward Medicare Advantage |
GLP-1 drugs show how the two columns blend. The list price is external. Coverage criteria, step therapy, and adherence programs are controllable, and they need pharmacy and medical claims joined in one dataset to show whether spend is buying outcomes. Joining those datasets is a data engineering task before it is a policy one.
Our view is that payers get more from tightening utilization levers than from fighting price, and providers get more from labor and denial work than from supply costs. This holds least for self-funded employers with thin network choice and for rural hospitals with little room to change labor mix. Both groups carry more external cost than the table suggests.
Is value-based care replacing fee-for-service?
Value-based care is growing but has not replaced fee-for-service, and payments carrying downside risk are a much smaller slice than payments tied to quality bonuses. In 2023, 28.5% of US health care payments flowed through downside-risk contracts, while 54.8% were still fee-for-service or fee-for-service with quality links, according to the Health Care Payment Learning & Action Network.
Medicare Advantage is the largest capitated channel, and an accountable care organization is the usual entry point in traditional Medicare. In 2025, 34.1 million people, 54% of eligible Medicare beneficiaries, were enrolled in Medicare Advantage (KFF, 2025).
We recommend taking on two-sided risk only when three things already exist:
- Attribution. You can name the patients you are accountable for each month, and the contract's attribution method matches the patients you treat.
- Claims-plus-clinical data. Payer claims, which often arrive weeks behind, are joined to EHR data through FHIR R4 and US Core APIs, so risk lists reflect current clinical status as well as billing history.
- Care management capacity. Care managers and EHR write-back workflows exist to act on the list. A risk score nobody follows up on changes no outcomes.
If one is missing, stay in upside-only shared savings and build it first. In our view the data layer is usually the slowest to build, and data engineering work should start before the contract is signed.
Before signing, get three things in writing: the benchmark method, the risk-adjustment model version, and the data-feed latency, since all three are required for outcome measurement.
This rule bends for small practices. With mostly commercial fee-for-service volume, panel sizes may be too small to absorb downside variance, and a pooled ACO spreads that risk.
How do remote patient monitoring and connected devices change care?
Remote patient monitoring moves routine measurement into the patient's home, so care teams receive continuous data between visits and must decide who acts on it. Enrolling patients is the easy part. Running the program is where it breaks, usually in one of three places:
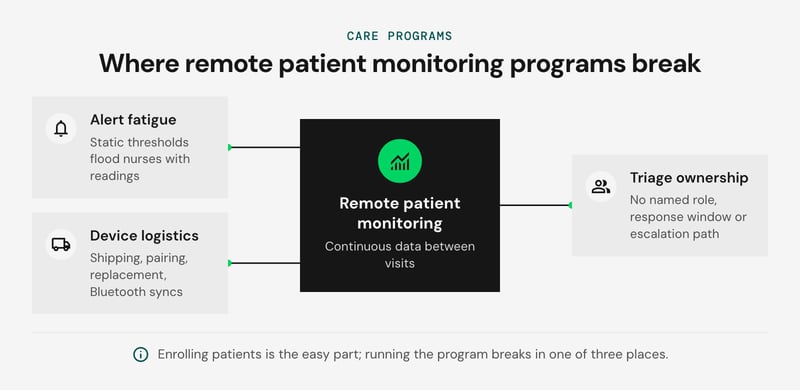
- Alert fatigue. Static thresholds flood nurses with out-of-range readings caused by a loose cuff or a skipped meal. We recommend per-patient thresholds and a tracked false-alert rate before enrollment scales.
- Device logistics. Shipping, pairing, replacement, and dropped Bluetooth syncs decide whether readings arrive at all.
- Triage ownership. With no named role, response window, and escalation path, an out-of-range reading sits in a dashboard. Writing readings back to the EHR over FHIR puts them in a queue someone already works.
Sync reliability is a logistics problem in software form. Working with Keto-Mojo since 2019, Netguru has helped build its connected health platform for blood glucose and ketone meters, where dependable syncing decides whether readings arrive.
The work covers stabilizing Bluetooth syncing, native iOS and Android apps from 2021, the MyMojo Health web app for users and healthcare professionals, a partner SDK, and a HIPAA-compliant Python backend. See the Keto-Mojo project.
What is hospital at home and what does it require?
Hospital at home delivers acute inpatient care in the patient's residence, and the CMS Acute Hospital Care at Home waiver lets approved hospitals bill it as an inpatient stay.
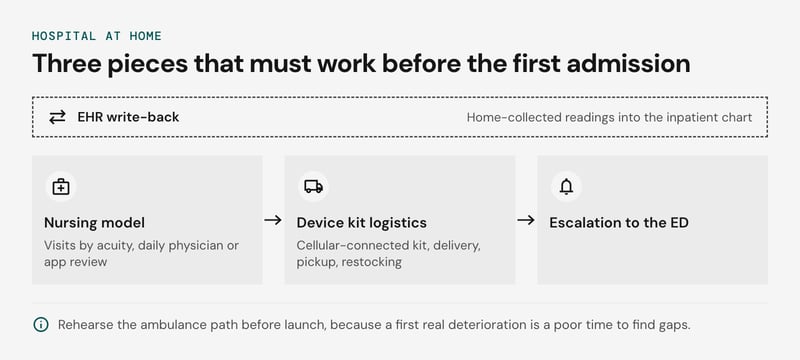
The waiver's end date has been extended by Congress more than once, so confirm the current one before building a business case. Three operational pieces must work before the first admission.
- Nursing model. Visit schedules start from the waiver's minimum daily clinician contact and add visits by acuity. Rosters are built around routes and drive times, with a physician or advanced practice provider reviewing each patient daily.
- Device kit logistics. Each kit typically holds a cellular-connected tablet, blood pressure cuff, pulse oximeter, scale, and thermometer. We recommend cellular connectivity because home Wi-Fi cannot be assumed. Delivery, pickup, cleaning, and restocking need an owner, as do lab samples traveling the other way.
- Escalation to the ED. A clinician is on call around the clock. Vital-sign thresholds trigger a defined response, and the transfer path to the ED is agreed with local EMS and a bed is held. Our view is that you should rehearse that ambulance path before launch, because a first real deterioration is a poor time to find the gaps.
EHR write-back from home-collected readings into the inpatient chart ties all three together.
How is virtual care settling into hybrid models?
Virtual care is settling into hybrid models where the visit type picks the channel: follow-ups, medication management, and talk therapy stay virtual, while physical exams, procedures, and first-time diagnostics return to the clinic.
What virtual retains is access. Patients reach specialists wherever they live, skip the commute and unpaid leave from work, and avoid exposure to infectious disease. Behavioral health shows this best, because therapy needs no equipment. Digital front door tools that make booking and follow-up this easy also feed patient satisfaction.
The split we recommend as a starting default:
| Visit type | Default channel | Reason |
|---|---|---|
| Therapy, medication management | Virtual | No physical exam needed |
| Chronic follow-up with device data | Virtual | Readings arrive between visits |
| Specialist consult after referral | Virtual first | Removes travel; escalate if imaging is needed |
| New symptoms, procedures | In person | Hands-on assessment |
Digital therapeutics fill the gaps between visits. They range from VR simulations for anxiety or social disorders to personalized apps that help diabetics track insulin, and current uses include chronic pain, asthma, and ADHD.
The engineering problem is routing. Build a triage rule that escalates from virtual to in person without making the patient rebook. In our view, batching virtual sessions into fixed clinic blocks can also reduce scheduling friction behind clinician burnout, though that depends on your staffing model. For vendor options, see our telemedicine platform comparison.
Why does FHIR interoperability still limit healthcare trends?
FHIR interoperability still limits healthcare trends because each EHR vendor applies the shared R4 standard differently, so every integration needs its own mapping and testing. Ambient documentation, remote monitoring, and hospital at home all depend on that plumbing.
Three failure modes stretch timelines:
- US Core variance. Vendors certify against the same R4 and US Core profiles, yet they differ in supported search parameters, extensions, terminology bindings, and how complete a resource is in practice. A query that works in one sandbox returns sparse data in another.
- SMART on FHIR scope gaps. An app registered for broad clinical scopes may be approved for a narrower set at a given health system. Discovering that late forces a redesign of the feature, not a config change.
- Write-back limits. Reading vitals or notes is the easy half. EHR write-back for observations, orders, or documents is often restricted by resource, vendor, or site policy, so a monitoring or scribe product may end up with a manual copy step.
On top of the technical gaps, each hospital runs its own security review, app approval, and sandbox-to-production promotion. Those steps tend to take longer than the code.
TEFCA gives networks a common framework for exchanging records between them, but it does not change how an individual EHR exposes its app APIs.
We recommend treating the first integration as a discovery exercise. Before committing a roadmap date, test the exact resources, scopes, and write paths your feature needs against each target EHR's production configuration. Where the gaps are large, a data engineering layer that normalizes vendor output keeps the product code stable.
How much does ransomware shape provider technology plans?
Ransomware attacks on providers shape technology plans mainly through downtime requirements: every AI or virtual care rollout has to keep working, or fail safely, when the EHR is offline.

Hacking and IT incidents are the largest category of breaches affecting 500 or more people reported to the HHS OCR breach portal.
The HIPAA Security Rule already requires a contingency plan covering data backup, disaster recovery, and emergency-mode operation (45 CFR 164.308(a)(7)), and new tools inherit that obligation.
We recommend adding three steps to the rollout checklist:
- Map vendor dependencies per tool. List the hosting region, identity provider, EHR API, and subprocessors behind each tool. An ambient scribe, for example, depends on the EHR write-back path and a cloud speech service, so two outages can stop it.
- Define a downtime mode for each tool. Scribes fall back to note templates, remote monitoring alerts route to phone triage, and hospital-at-home escalations go to a staffed call line.
- Rehearse restores. Run tabletop exercises and timed recovery drills that include the read-only EHR downtime view.
The pandemic exposed how much hospitals rely on external suppliers, and software vendors are now part of that chain. A vendor that cannot show its own recovery time objective is a supply risk.
How to track healthcare industry trends
Track healthcare industry trends with a short list of primary sources, each reviewed on the cadence at which it publishes. The CMS National Health Expenditure projections, the FDA AI-enabled medical device list and TEFCA exchange data cover cost, AI and interoperability.
The table maps each trend to a source and a leading indicator:
| Trend | Source | Review cadence | Leading indicator |
|---|---|---|---|
| Medical cost trend | CMS National Health Expenditure projections | Annual | Projected spending growth by payer and service category |
| Interoperability | ASTP/ONC data briefs; TEFCA participation updates | Twice a year | Share of providers exchanging data across networks, and which TEFCA exchange purposes are live |
| AI in diagnostics | FDA AI-enabled medical device list | Quarterly | New authorizations by specialty |
| Ambient documentation | Peer-reviewed studies, such as JAMA Network Open | Quarterly | Measured time in notes and clinician burnout outcomes |
| Ransomware | HHS OCR breach portal | Monthly | Hacking-related breaches at providers and business associates |
| Workforce | AHA and HRSA reports | Annual | Vacancy and staffing-gap projections |
We suggest one named owner per row and a quarterly review that moves each trend between "watch" and "act". A trend graduates when two indicators move together, for example new FDA authorizations in your specialty plus a payer or TEFCA exchange route to pay for or feed the product. Quarterly reviews suit scale-ups; a small team can drop to twice a year.
For a technology-by-technology view, see our 10 healthtech trends.

FAQ
What are the top 3 trends in the healthcare industry?
What are some current health trends?
What are the five trends in health care?
Turn a healthcare trend into a scoped pilot
Healthcare trends pay off when a team picks one, names a clinical owner and tests the integration before committing a roadmap date. Netguru builds healthcare software, including connected-device, remote monitoring and EHR-integrated products. If you want help scoping the first pilot, get an estimate for your project.


